What is Total Knee Replacement?
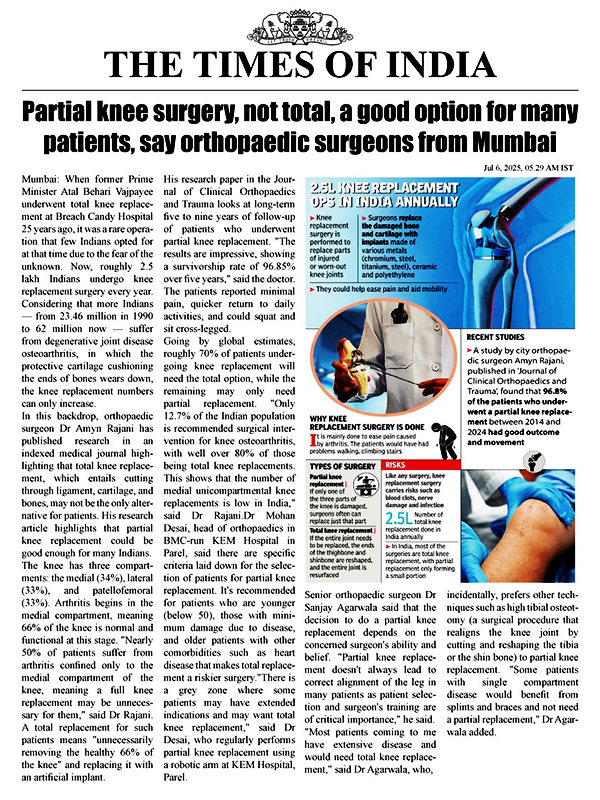
Total knee replacement is considered when advanced knee arthritis causes persistent pain, stiffness and loss of function despite appropriate non-surgical care. During total knee replacement surgery, damaged joint surfaces are removed and resurfaced with artificial components. A total knee replacement procedure is usually considered when arthritis affects several parts of the joint and everyday activities have become difficult.
What Is Total Knee Replacement?
Total knee replacement, also called total knee arthroplasty, resurfaces the damaged ends of the femur and tibia. The kneecap may also be resurfaced when appropriate. It replaces worn bearing surfaces rather than the whole knee as an organ.
In a total knee replacement operation, metal components resurface the femur and tibia, with a polyethylene insert between them. A plastic patellar component may also be used when clinically appropriate.
When Is Total Knee Replacement Surgery Considered?
Total knee replacement surgery is usually discussed when knee osteoarthritis causes persistent pain, stiffness, difficulty walking, disturbed sleep or loss of independence despite sensible non-operative care. Rheumatoid arthritis and post-traumatic arthritis can also damage the joint enough to make a total knee replacement procedure appropriate.
The decision should not be based on an X-ray alone. A total knee replacement surgeon will consider symptoms, examination findings, X-rays, general health, muscle strength, expectations and how much daily life is affected.
Who May Not Be Suitable?
A total knee replacement operation may need to be delayed or reconsidered if there is an active infection, poorly controlled medical illness, severe skin problems around the knee or another condition that makes surgery unusually risky. Some people with milder, compartment-specific disease may be better suited to partial knee replacement or another treatment.
What Happens During a Total Knee Replacement Procedure?
Anaesthesia and Hospital Stay
A total knee replacement may be performed under general anaesthesia or spinal anaesthesia, often with sedation. The anaesthetist may also use nerve blocks or local anaesthetic techniques to support pain control after surgery. The safest option depends on general health, medicines, the surgical plan and patient preference.
Hospital stay is usually short. NHS guidance says most people leave hospital 1 to 3 days after knee replacement once the wound is healing well and they can move around safely. Some enhanced-recovery pathways allow earlier discharge for suitable patients.
During total knee replacement surgery, the surgeon exposes the knee, removes damaged cartilage and a measured amount of bone, then prepares the femur and tibia for the implants. Trial components may be used to check alignment, stability and movement before the final components are fixed.
The total knee replacement procedure can be performed with conventional instruments, computer navigation or robotic assistance.
What Are the Main Implant Components?
- The tibial component covers the top of the tibia and usually includes a metal baseplate with a polyethylene insert.
- The femoral component covers the lower end of the femur and is usually metal.
- The patellar component, when used, resurfaces the underside of the kneecap with polyethylene.
Modern total knee replacement implants are durable, but lifespan varies with design, fixation, alignment, activity, body weight and health.
Robotic Total Knee Replacement
Robotic total knee replacement uses computer-assisted planning and robotic guidance to help the surgeon execute bone cuts and implant positioning within defined boundaries. It does not perform the operation autonomously.
A 2026 network meta-analysis of 36 studies involving 2,841 patients found that robotic systems differed in their strengths across alignment, function, blood loss and range of motion, while conventional TKA remained faster to perform. A 2025 meta-analysis also found no significant difference in implant survivorship between robotic and conventional TKA. Robotic total knee replacement is therefore best viewed as a surgical tool, not a guarantee of a better result.
Bilateral Total Knee Replacement
Bilateral total knee replacement means replacing both knees, either during one anaesthetic or as staged procedures. The choice depends on overall health, heart and lung status, blood-loss risk, mobility and rehabilitation capacity. For some patients, staging the operations is safer and makes recovery easier to manage.
Recovery After Total Knee Replacement Surgery
Walking usually starts soon after total knee replacement surgery with support from a walker or crutches, depending on the hospital protocol and the patient’s stability. Physiotherapy then focuses on swelling control, knee movement, quadriceps strength, balance and safe walking.
Basic daily activities may become easier over several weeks, while strength and endurance can improve for months. Health, fitness, body weight, diabetes, smoking, previous surgery and rehabilitation all influence recovery after a total knee replacement procedure.
When Can You Use Stairs, Drive and Return to Work?
Stairs are usually practised once strength and balance are adequate. Driving depends on the operated knee, reaction time, pain, mobility and whether medicines that impair alertness are still needed.
Desk-based work may be possible earlier than jobs involving lifting, prolonged standing, climbing or kneeling. A total knee replacement surgeon should review healing and function before giving individual advice.
What Are the Benefits of Total Knee Replacement?
For suitable patients, total knee replacement surgery can reduce arthritis-related pain, improve movement and make everyday activities easier. It may also correct deformity and improve stability. Results vary, and some patients still have stiffness or discomfort.
Risks and Warning Signs
Expected early symptoms after total knee replacement surgery include pain, swelling, bruising and stiffness. Recognised complications include infection, blood clots, fracture, nerve or blood-vessel injury, wound problems, persistent pain, stiffness, implant loosening or wear and the need for revision surgery.
Seek prompt medical advice for increasing wound redness or drainage, persistent fever, worsening calf swelling, chest pain, breathlessness, sudden severe pain or new numbness.
Are There Alternatives to Total Knee Replacement Surgery?
Yes. Total knee replacement is not the first treatment for every painful knee. Depending on the diagnosis and severity, options may include physiotherapy, activity changes, weight management, medicines, injections, bracing or observation.
If arthritis is limited to one compartment, partial knee replacement may be appropriate. High tibial osteotomy can be considered in selected patients with alignment-related overload, while knee arthroscopy has a limited role in established osteoarthritis.
What Current Research Shows
Evidence continues to evolve. A 2024 meta-analysis found more accurate prosthetic alignment with robotic-assisted total knee replacement but no consistent overall clinical advantage. A 2026 network meta-analysis found that different robotic systems performed differently across several outcomes. Taken together, the evidence supports matching technology to the patient and surgical problem rather than assuming robotics automatically produces a better result.
What Dr Amyn Rajani’s Research Adds
Dr Amyn Rajani’s scientific publications and Google Scholar profile include research on pain control, alignment and challenging situations in total knee arthroplasty.
Duloxetine and Pain After Bilateral Total Knee Replacement
In a 2024 prospective, double-blinded, randomised, placebo-controlled trial, Dr Rajani and colleagues studied 106 patients undergoing single-setting bilateral total knee arthroplasty. The study examined low-dose duloxetine as part of postoperative pain management in patients without central sensitivity.
The trial is relevant because pain can affect early mobilisation after bilateral total knee replacement. It does not mean duloxetine suits every patient; medication decisions remain individual.
Varus Deformity and Long-Term Outcomes
Dr Rajani and colleagues also reported 12-year outcomes in patients who underwent total knee replacement with varus deformity. Their work evaluated long-term function and alignment rather than treating every knee as mechanically identical.
More recently, their postero-central slice osteotomy research addressed resistant tight extension gaps during posterior-stabilised total knee arthroplasty for varus osteoarthritis. The work highlights why difficult knees may need tailored balancing rather than one standard approach.
Frequently Asked Questions
How painful is total knee replacement surgery?
Pain is expected after total knee replacement surgery, especially early on. Modern pain plans may combine anaesthesia techniques, prescribed medicines, swelling control and rehabilitation.
How long does total knee replacement recovery take?
Basic recovery after total knee replacement usually takes several weeks, while strength and endurance may improve for months. Health and rehabilitation progress influence the timeline.
How long does a total knee replacement last?
NHS patient guidance notes that a total knee replacement can last 20 years or more. A long-term systematic review also reported high survivorship beyond 15 years. Implant life still varies with age, activity, body weight, fixation, alignment and design, so no individual lifespan can be guaranteed.
Is robotic total knee replacement better?
Not automatically. Robotic assistance may improve alignment precision, but current evidence does not show one universal advantage for every patient. Surgeon judgement, implant choice, knee anatomy and rehabilitation still matter.
Can both knees be replaced together?
Yes, bilateral total knee replacement may be possible for selected patients. Careful medical assessment is essential because the physiological demands are greater.
What happens if a total knee replacement fails?
Revision surgery after total knee replacement may be needed if an implant loosens, wears, becomes infected or remains persistently painful. The cause must be investigated before treatment is planned.
Will I need physiotherapy?
Yes. Physiotherapy after total knee replacement commonly helps restore movement, strength, balance and safer walking.